


US tax law offers up to US$85 for every tonne of carbon dioxide captured and stored at an industrial source such as a power plant, and up to US$180 for a tonne pulled from the air. In the rainforests of Indonesian Borneo, communities have kept carbon out of the atmosphere for a fraction of that price with a system anchored in health care.
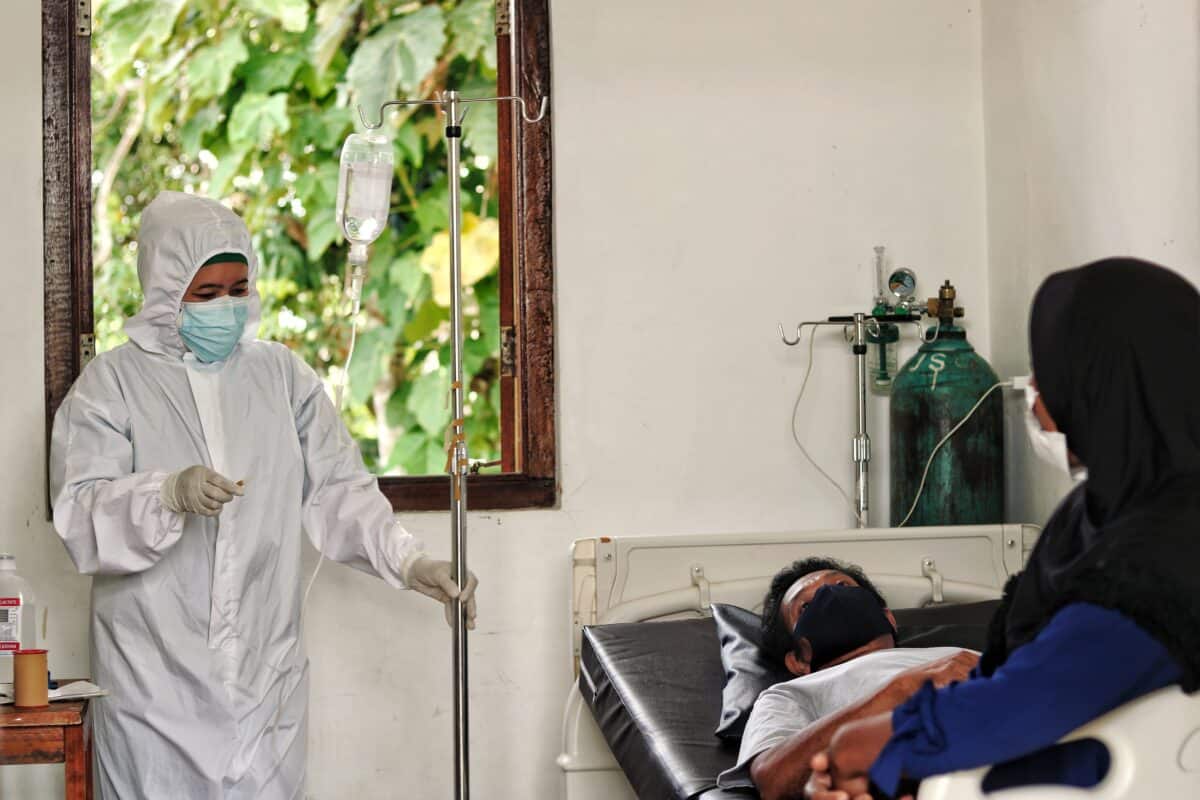
Indonesia holds some of the most carbon-dense forests on Earth, and in the early 2000s logging was consuming them. The international nonprofit Health In Harmony takes a different approach to conservation: through its Radical Listening model, it asks rainforest communities to design forest protection strategies, and then invests precisely in their solutions. During 400 hours of Radical Listening with nearly 500 community representatives around Gunung Palung National Park, communities designed a system to protect forests that linked access to affordable, quality health care with job opportunities.
A clinic was established on the rainforest edge. Discounts for care increased as a village’s logging rates fell. Families could pay for care with tree seedlings, manure, handicrafts, or labor. Salaried community forest guardians monitored logging activity. A chainsaw buyback initiative combined with training in small business development and organic farming justly transitioned hundreds of loggers into safer, better-paying, forest-friendly occupations.
The Carbon Math

The communities were right. A decade of data (2008-2018), published in the Proceedings of the National Academy of Sciences, found forest loss in the park was 70% lower than in a synthetic control built from other Indonesian national parks. Households relying on logging as their main income fell 90%. Communities averted the loss of 27 square kilometers of rainforest holding 0.59 million tonnes of above-ground carbon, the carbon dioxide equivalent of taking 470,000 cars off the road for a year. At the peak 2019 European carbon price, the measured carbon stock would have been worth approximately US$65 million, twelve times the US$5.2 million total investment: roughly US$2.40 per tonne of carbon dioxide. This valuation excludes below-ground carbon, peat and regrowth, which the study did not measure. And this ignores the health co-benefits – over 28,000 patients gained access to quality care. Diagnosed cases of malaria, tuberculosis, and diabetes fell among the clinic’s catchment, as did infant mortality. Tuberculosis declined within the community even as it rose across the region.
Their system also held under stress. When COVID-19 hit West Kalimantan, incomes collapsed, fertilizer prices spiked, and health services buckled. A Lancet Planetary Health study found the forest-loss gap between supported villages and unsupported ones widened, from 52% to 68%. In unsupported villages, forest loss rose and fell with timber prices. In supported villages, where community-designed systems were in place, that link was shown to no longer exist.
Borneo is not an anomaly. In every rainforest where we have practiced Radical Listening– across Madagascar, the Brazilian Amazon, and the Congo Basin- communities typically anchor their system designs in access to health care alongside just livelihoods transition.

Health Systems as Climate Infrastructure

Communities living in tropical forest areas are often positioned in various levels of tenure. What remains constant is the external pressure from extractive industries to negotiate unfavourable concessions, often taking advantage of community vulnerabilities such as a lack of health infrastructure. By making healthcare accessible and addressing the pressures that drive forest loss, community-led approaches can improve people’s lives while helping keep forests standing.
The economics are compelling. Securing Indigenous land tenure in Bolivia, Brazil and Colombia could prevent 42.8 to 59.7 million tonnes of carbon dioxide emissions a year, at US$2 to US$12 a tonne. Protecting Indigenous territories in the Brazilian Amazon could help prevent over 15 million cases of respiratory and cardiovascular disease a year; this doesn’t include the benefit of pandemic prevention through a reduction in spillover exposure.
In 2024, 147 governments agreed that Indigenous Peoples and local communities co-design and governance can increase the benefits of conservation.
Yet of the US$2.35 billion donors delivered against a US$1.7 billion forest tenure and land management pledge, the share reaching Indigenous Peoples and local community organizations directly fell from 10.6% in 2023 to 7.2% in 2025. From governments, which supplied 74% of last year’s funding, it was under 1%. This isn’t an accounting error. It’s the architecture of a system that ignores the true value of Indigenous Peoples’ ecosystem stewardship.
Counting the Wrong Things

Most climate finance still files health care under “co-benefits”: welcome, optional, and first to be cut. It also counts money that never reaches the forest.
The Global Biodiversity Framework Fund (GBFF), the Global Environment Facility, and Brazil’s Tropical Forest Forever Facility now carry targets to direct 20% of their total funds to Indigenous Peoples and local communities. This is historic.
Unfortunately, while the GBFF reports 31.9% of its funding has “supported actions by” Indigenous Peoples and local communities, independent analysis of its first forty initiatives found only one project demonstrably directing resources to Indigenous Peoples and local communities, approximately 4% of all committed funds. A 2025 IIED study of GEF projects in five countries found “little evidence that funding was arriving at the local level.” Accounting standards for these historic targets must be redefined by Indigenous Peoples themselves according to their own governance practices.
Where to Start
This month in Yerevan, governments at the UN biodiversity summit, COP17, will negotiate how to protect nature and pay for it. Two decisions could change the game, namely: recognise community-designed healthcare and livelihood programmes as ways to protect and restore nature, and ensure that funding channelled through international intermediaries does not count toward these Funds’ new 20% targets.
In Washington, the TREE Act (H.R. 8744), introduced in May, would bar US imports of commodities linked to deforestation, matching European Union rules that apply from December. Emissions averted by community-designed systems anchored in health care are exactly the evidence it invites.
The communities of Gunung Palung were not designing a carbon project. They were designing a new health system that ties their wellbeing to the wellbeing of their rainforest: one that treats nature-positive livelihoods as a health intervention, recognizes land tenure as public health infrastructure, and measures success in the long-term vitality of people and forest together. For those of us dedicated to reversing the climate crisis and nature’s collapse, reimagining health systems as the climate solutions they are might be the biggest, most feasible, and cost-effective opportunity of the 21st century.







